Quick facts
| Item | Summary |
| Procedure type | Metabolic gastrointestinal surgery |
| Purpose | To improve glycaemic control and associated metabolic conditions in selected adults with type 2 diabetes |
| Surgical approach | Laparoscopic or robotic-assisted, under general anaesthesia |
| Combined with | A sleeve gastrectomy whose size is adjusted to the patient’s BMI; performed as a jejunal (non-diverted) or duodenal (diverted) version |
| Eligibility | Decided individually: diabetes duration and control, BMI, pancreatic reserve (C-peptide), and overall fitness for surgery |
| Expected outcomes | Published series report lower HbA1c and reduced medication needs in many patients; remission is not guaranteed |
| Recovery | Several days in hospital, a staged diet over 4 to 6 weeks, and long-term metabolic follow-up |
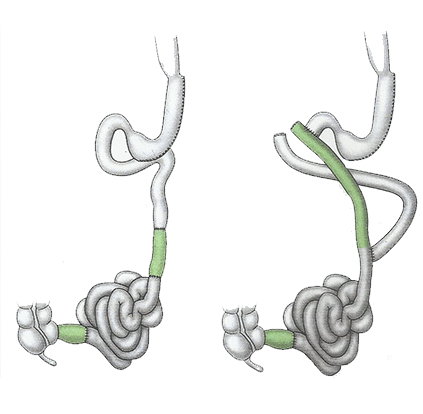
Laparoscopic ileal interposition with sleeve gastrectomy is a metabolic procedure for type 2 diabetes, hypertension, dyslipidaemia and excess weight. It has two components. A sleeve gastrectomy reduces the size of the stomach. A segment of the terminal ileum, the last part of the small intestine, is then moved closer to the stomach so that it meets food earlier after a meal.
No intestine is removed. The ileal segment keeps its own blood supply and is relocated, not bypassed, so the total length of bowel available for absorption is preserved. Each step of the operation has an intended hormonal target, described under the mechanism section below.
Two versions are described in the literature:
The idea grew out of animal research. In the early 1980s, Koopmans and Sclafani showed in rats that transposing a short segment of ileum reduced weight. In 1999, Dr Edward E. Mason proposed that ileal transposition could be well suited to treating type 2 diabetes through its effect on GLP-1, while advising that it should await well-designed safety and efficacy studies (Mason, Obes Surg 1999).
The Brazilian surgeon Dr Aureo L. De Paula, working in Goiânia, developed the laparoscopic operation in humans, combining ileal interposition with sleeve gastrectomy. He began operating in late 2003 and first published the technique in 2005 and 2006, calling it the “neuroendocrine brake” (SSAT 2006 abstract). Indian surgeons, notably in Hyderabad, later adapted it with a BMI-adjusted sleeve for patients with lower body weight.
Conventional bariatric procedures, such as sleeve gastrectomy, Roux-en-Y gastric bypass and one-anastomosis (mini) gastric bypass, are designed mainly to treat obesity. Improvement in diabetes is a major and well-documented benefit. Ileal interposition was designed with diabetes as the primary target, aiming to change gut hormone signalling rather than to produce maximum weight loss or malabsorption.
The evidence bases differ considerably. Sleeve gastrectomy and gastric bypass together account for about 90% of metabolic operations worldwide and have randomised trials and long-term data behind them (ASMBS/IFSO 2022). Ileal interposition has been studied mainly in single-centre observational series, largely in patients with BMI below 35 kg/m². The first Diabetes Surgery Summit advised that newer operations, including ileal interposition, be performed within approved and registered studies (DSS summary).
Ileal interposition is therefore not a routine or first-line treatment for type 2 diabetes. It may be discussed for carefully selected patients after a full assessment of established medical and surgical options.
Suitability is decided individually by the surgeon together with a diabetologist or endocrinologist. Published protocols have generally included adults who meet the following conditions:
Patients are generally not considered if they have type 1 diabetes or autoimmune diabetes (positive GAD antibodies), absent C-peptide, pregnancy, severe heart, lung, liver or kidney disease, an active eating disorder, or previous major gastrointestinal surgery (Kota et al. 2012; Celik et al. 2015).
Ileal interposition has been studied in people with type 2 diabetes who are not obese. This is relevant in India, where type 2 diabetes often develops at a lower BMI. For this reason, the 2022 ASMBS/IFSO guidelines use a lower threshold for Asian patients, recommending that metabolic surgery be offered from a BMI of 27.5 kg/m² (ASMBS/IFSO 2022).
Published ileal interposition series have included patients with BMI between about 19 and 35 kg/m². One series of 454 patients had a mean BMI of 29.7 kg/m², ranging from 19 to 34.8 (DePaula et al. 2011). Other studies have enrolled patients with BMI 23 to 34 kg/m². These ranges describe who was enrolled in those studies. They are not eligibility criteria.
For patients below conventional BMI thresholds, evidence comes mainly from observational studies. The decision to operate in this group needs particularly careful discussion of expected benefit, risk and alternatives.
An Indian series reported better remission in patients with shorter diabetes duration, better C-peptide response and higher BMI (Kota et al. 2012).
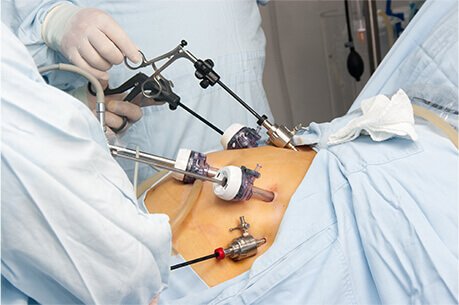
The operation is performed through several small abdominal incisions, either laparoscopically or with robotic assistance. It combines a sleeve gastrectomy with relocation of an ileal segment, and it involves both the upper and lower abdomen. Operating time is longer than for a sleeve gastrectomy alone, usually several hours.
The patient is given general anaesthesia and placed supine (lying on the back). Because the operation is carried out in both the upper abdomen (stomach) and the lower abdomen (ileum), the operating table is tilted during the procedure. A head-up tilt is used for the sleeve gastrectomy and a head-down or lateral tilt for the bowel work. Port positions may also be adjusted between the two stages.
A sleeve gastrectomy is performed in the standard manner. The stomach is divided along its length over a calibration tube, removing the fundus and much of the greater curvature. In patients who are not obese, a relatively loose (wider) sleeve is created, or only the fundus is removed, so that food intake is less restricted and excessive weight loss is avoided (Celik et al. 2015).
In the published technique, the last 30 cm of ileum before the ileocaecal valve is preserved. A segment of about 170 cm of distal ileum is isolated on its own blood supply and moved upward (Celik et al. 2015). Three anastomoses (joins) are made, using staplers or sutures:
Ileo-ileal anastomosis: restores continuity of the remaining ileum.
Proximal anastomosis: connects the upper end of the segment to the jejunum, about 50 cm from the ligament of Treitz (jejunal version), or to the first part of the duodenum (diverted version).
Distal anastomosis: connects the lower end of the segment to the jejunum.
Gaps in the mesentery are closed to reduce the risk of internal hernia. Some centres also remove the gallbladder at the same operation because gallstones are common after this surgery.
Both approaches perform the same internal operation. They differ in how the surgeon controls the instruments.
| Feature | Laparoscopic | Robotic-assisted |
| Surgical access | Five to six small ports | Similar number of ports; the robotic arms dock to them |
| Instruments | Rigid, straight instruments with limited articulation | Wristed instruments with a wider range of movement |
| Visualisation | High-definition 2D or 3D camera, held by an assistant | Stable 3D high-definition view, controlled by the surgeon |
| Surgeon control | Direct handling of instruments at the table | From a console, with tremor filtering and motion scaling |
| Hand-sewn anastomoses | Technically demanding | Wristed instruments can make intracorporeal suturing easier |
| Availability and cost | Widely available | Fewer centres; higher equipment and consumable costs |
| Recovery | Same principles for both | No published evidence shows faster recovery for ileal interposition |
No comparative studies of laparoscopic versus robotic ileal interposition were found. The choice depends on the surgeon’s experience, the patient’s anatomy and the facilities available.
Ileal interposition is based on the “hindgut hypothesis”: delivering nutrients earlier to the distal small intestine increases the release of hormones that improve glucose control. The terminal ileum is rich in L-cells, which secrete glucagon-like peptide-1 (GLP-1) and peptide YY (PYY). Moving the ileum upward exposes these cells to food within minutes of eating.
The diverted version also keeps food away from the duodenum, which is the basis of a second, “foregut” hypothesis. The sleeve gastrectomy adds its own hormonal and mechanical effects. In people studied after surgery, insulin sensitivity was restored and the glucose sensitivity of insulin-producing β-cells roughly doubled, through mechanisms partly independent of weight loss (DePaula et al. 2011).
| Hormone | Main source | Role in glucose regulation | Expected change after surgery |
| GLP-1 | L-cells, ileum and colon | Increases insulin release when glucose is high, suppresses glucagon, slows stomach emptying, promotes fullness | Increased; rises after meals were reported in operated patients |
| PYY | L-cells, ileum and colon | Promotes fullness and reduces food intake | Increased |
| GIP | K-cells, duodenum and upper jejunum | Stimulates insulin release; this effect is blunted in type 2 diabetes | Variable; diverting the duodenum may reduce stimulation |
| Glucagon | Alpha cells of the pancreas (not the gut) | Raises blood glucose; levels are often too high in type 2 diabetes | May be lowered indirectly by GLP-1; evidence in operated patients is mixed |
| Ghrelin | Stomach, mainly the fundus | Stimulates appetite; may restrain insulin secretion | Reduced, because the sleeve removes the fundus |
In 58 patients with BMI 20 to 34 kg/m² studied at a mean of 16 months, GLP-1 and PYY rose after both versions of the operation and ghrelin fell significantly (DePaula et al. 2009).
GIP, glucagon and ghrelin are sometimes grouped together as gut hormones that cause insulin resistance, but their roles differ. GIP is an incretin that normally stimulates insulin release, and glucagon comes from the pancreas. A more accurate summary is that the operation aims to increase GLP-1 and PYY, reduce ghrelin and, in the diverted version, reduce nutrient contact with the duodenum.
The sleeve gastrectomy contributes in three ways that are reasonably well established:
Other questions remain open. The relative contributions of the sleeve, the ileal segment, duodenal exclusion and weight loss to the overall result have not been separated in human trials. Changes in bile acid circulation and the gut microbiome have also been proposed, but their importance is not yet established.
Published series report substantial improvement in blood glucose, and in many patients a reduction or withdrawal of diabetes medication. Results vary with diabetes duration, pancreatic reserve and BMI, and they come largely from observational studies.
Improved control and remission are different outcomes:
Key published results:
| Study | Patients | Follow-up | Reported result |
| DePaula et al. 2012, Brazil | 202, BMI below 35 | 2 to 5 years | HbA1c below 7% in 89.9%; below 6.5% in 78.3%; 86.4% off diabetes medication |
| Kota et al. 2012, India (diverted version) | 32, BMI 22.4 to 39.5, diabetes for 5 to 30 years | Mean 13 months | Remission (HbA1c below 6.5% without medication) in 70.5% |
| Goh et al. 2016, systematic review | Pooled studies | Varied | Remission 47% to 95.7% across studies; about 65% where a fixed HbA1c threshold defined remission |
The wide range reflects different definitions of remission and different patient groups.
Improvements beyond glucose control have been reported, but not in every patient:
These figures come from small or single-centre series with follow-up of one to five years. Individual results may differ.
Type 2 diabetes is a progressive condition, so long-term follow-up is essential after any metabolic operation. Unpublished conference data from one Indian centre suggest that remission is maintained in many patients up to 10 years, with lower durability after the jejunal version than after the diverted version (Ugale, IFSO presentation). These data have not been peer reviewed.
The evidence has important limitations:
Ileal interposition should not be regarded as a guaranteed cure for type 2 diabetes.
Ileal interposition is a complex operation with three intestinal joins as well as a stapled stomach. Its complication rate is higher than that of simpler procedures such as sleeve gastrectomy alone. Many patients also have long-standing diabetes and heart or kidney disease, which raises surgical risk.
Two large published series give an indication of early risk:
| Series | Patients | Mortality | Complications | Reoperation |
| DePaula et al. 2011, Brazil, BMI below 35 | 454 | 0.4% | Major 6.4%; minor 11.2% | 1.7% |
| Celik et al. 2015, Turkey, diverted version | 360 | 0.27% surgery-related | Surgical 6.1%, including leaks 2.2% | 1.9% |
Contact the surgical team immediately, or go to the nearest emergency department, if you notice any of the following after surgery:
For urgent concerns, call the clinic on +91 7770001900. In an emergency, call 112 or go to the nearest hospital emergency department.
For urgent concerns, call the clinic on +91 7770001900. In an emergency, call 112 or go to the nearest hospital emergency department.
Recovery involves close monitoring in hospital, a staged return to normal eating over several weeks, careful adjustment of diabetes medicines and long-term follow-up.
After surgery, patients are monitored for pulse, blood pressure, temperature, blood glucose, fluid balance and signs of early complications. Walking is encouraged from the first day, and blood-thinning injections and compression stockings help prevent clots. Sips of water are usually started once the team is satisfied that the joins are healing, sometimes after a contrast X-ray.
Published series report mean hospital stays ranging from about 3 to 9 days (Tinoco et al. 2011; Celik et al. 2015). Most people return to desk-based work within 2 to 4 weeks and avoid heavy lifting for about 4 to 6 weeks.
The diet progresses in stages to allow the stomach and intestinal joins to heal:
Throughout recovery, sip fluids steadily between meals to stay hydrated, and meet the daily protein target set by the dietitian. Eat slowly, stop at the first sign of fullness, and avoid sugary foods and drinks. Vitamin and mineral supplements, such as a multivitamin, vitamin B12, iron, calcium or vitamin D, should be taken as recommended by the treating team.
Blood glucose can fall quickly after surgery, often before much weight is lost. Doses of insulin and some tablets, particularly sulfonylureas, often need to be reduced or stopped to prevent low blood sugar. Some medicines, such as SGLT2 inhibitors, are usually paused around the time of surgery.
All changes to diabetes medication must be made by the treating clinician. Patients should not stop or change medicines on their own. Regular home glucose monitoring is important, particularly in the first weeks.
Typical follow-up includes:
| Potential advantages | Limitations |
| Investigated specifically as a metabolic operation for type 2 diabetes | A complex operation with three intestinal joins and a longer operating time |
| May improve glycaemic control in selected patients | Not suitable for every person with type 2 diabetes |
| May reduce or remove the need for diabetes medication in some patients | Carries surgical and postoperative risks, including leaks and strictures |
| Has been studied in selected patients with lower BMI, including some who are not obese | Outcomes vary considerably between individuals |
| Relocates rather than bypasses bowel, so absorption is largely preserved | Long-term evidence is limited and largely from single centres |
| May improve blood pressure, lipids and urinary albumin in some patients | Requires lifelong medical monitoring, supplements where advised and lifestyle management |
Type 2 diabetes can be managed medically, with established metabolic operations, or, in selected cases, with newer procedures such as ileal interposition. The right option depends on the individual patient.
| Feature | Medical management | Sleeve gastrectomy | Gastric bypass (Roux-en-Y or one-anastomosis) | >Ileal interposition with sleeve |
| Approach | Diet, activity and medicines, including metformin, GLP-1 receptor agonists, SGLT2 inhibitors and insulin | Removes about three-quarters of the stomach | Small stomach pouch joined to the small intestine, bypassing the duodenum and part of the jejunum | Sleeve plus relocation of an ileal segment |
| Main purpose | Glucose and cardiovascular risk control | Weight loss with metabolic benefit | Weight loss and metabolic control | Metabolic control, with moderate weight loss |
| Invasiveness | Non-surgical | Moderate: stapling only | Higher: stapling and one or two intestinal joins | Highest of these: stapling and three intestinal joins |
| Guideline status | First-line for all patients | Endorsed by international guidelines | Endorsed by international guidelines | Supported by observational studies; not among guideline-endorsed standard procedures |
| Typical suitability | All patients | Metabolic surgery BMI thresholds (from 27.5 kg/m² in Asian patients) | Metabolic surgery BMI thresholds; often preferred when reflux or diabetes is significant | Selected patients after specialist assessment, mostly studied at BMI below 35 kg/m² |
| Follow-up | Regular review and medication adjustment | Lifelong nutritional and metabolic follow-up | Lifelong, with greater supplement needs | Lifelong nutritional and metabolic follow-up |
No single treatment is safer or more effective for everyone. Related pages: Surgery for Diabetes overview, Sleeve Gastrectomy, Roux-en-Y Gastric Bypass, Mini Gastric Bypass, Laparoscopic Duodenojejunal Bypass and Smart Nutrition.
The total cost depends on several factors:
Insurance coverage for metabolic surgery varies by insurer and policy, so patients should check with their provider. For an individual estimate, please contact the clinic after your consultation.
Prof. (Dr.) Atul N.C. Peters is Vice Chairman of the Department of Bariatric, Minimal Access and Robotic Surgery at Max Smart Super Speciality Hospital, Saket, New Delhi. He has close to three decades of surgical experience, with a focus on robotic gastrointestinal, bariatric and metabolic surgery, and serves as a robotic surgery proctor.
If you have type 2 diabetes and would like to know whether metabolic surgery is appropriate for you, you can book a consultation with Dr. Atul Peters. The consultation includes a review of your diabetes history, medications, tests and overall health, and a discussion of all suitable options, both medical and surgical.